When Does a Doctor Suspect Pneumonia?
Can Two Clinicians Use Different Words for the Same Lung Infection?
Yes. Chest infection is a broad description. Pneumonia is a more specific diagnosis involving inflammation in the lung, usually caused by infection. Bronchitis, which affects the larger airways, is another common chest infection. If a clinician initially describes a chest infection and later diagnoses pneumonia, that change in wording alone cannot tell you whether the illness has worsened or whether more information has made the diagnosis clearer.
If someone is gasping, choking or too breathless to speak, call 999. Emergency signs also include pale, blue or blotchy lips or skin, sudden confusion, or a baby who is floppy or cannot be woken. NHS pneumonia guidance also directs people coughing up blood to emergency care. Do not wait for a chest X-ray, a home oxygen reading or a particular colour of phlegm before seeking help with severe symptoms.
Where in the Chest Is the Problem?
Follow a breath in. Air passes through the windpipe into branching tubes and eventually reaches tiny air sacs called alveoli. Across their thin walls, oxygen enters the bloodstream and carbon dioxide leaves it. Inflammation of the larger tubes can make them produce mucus and trigger a persistent cough. In pneumonia, inflammation farther into the lung can affect the air spaces through which gas exchange normally takes place.
That difference helps explain why somebody can look quite ill even when coughing is only one part of the story. Breathing more quickly or putting more effort into each breath can be a way of compensating for reduced efficiency. The heart and the rest of the body are involved in getting oxygen where it needs to go. An assessment therefore extends beyond listening for a noisy cough.
There is no useful rule that a dry cough means one condition and a productive cough means the other. Fever, tiredness, discomfort when breathing and shortness of breath can occur in overlapping combinations. Some people produce coloured mucus. Some do not. The location of inflammation inside a chest cannot be determined reliably by looking at a tissue.
Does a Chest Infection Turn Into Pneumonia?
Sometimes a person with a respiratory illness deteriorates and develops pneumonia. A viral infection can precede a secondary bacterial infection. Sometimes pneumonia was present when the person first became unwell and is recognised only later. In other cases the symptoms are due to bronchitis and recover without pneumonia ever developing. There is no obligatory sequence through which every winter cough progresses.
The timeline is still useful. Tell a clinician when the illness started, whether you were improving and what changed. A fever returning after an apparent recovery, increasing breathlessness or a new inability to manage ordinary activities are observations that can influence what happens next. They have greater clinical value than trying to decide at home which day a general illness supposedly acquired a new label.
The distinction matters for reassurance too. A cough can persist after the most acute part of an infection has passed. Persisting does not automatically mean deteriorating. Conversely, a person who develops significant breathing difficulty over a short period needs assessment even if they have been coughing for only a day. How someone is breathing now takes priority over completing a timetable found online.
What Does a Clinician Check?
A clinician can ask about breathlessness at rest and on exertion, fever, chest pain, appetite, fluid intake and changes in alertness. Age, pregnancy where relevant, immune suppression, heart disease, lung disease and a person’s usual level of function can change the level of concern. An older adult who is unexpectedly confused or weak may need prompt attention even without a dramatic account of cough.
Observations commonly include breathing rate, temperature, heart rate and oxygen saturation. Blood pressure and mental state can help assess severity. Listening to the chest may reveal sounds suggesting a particular area of lung is affected. The clinician brings these pieces together. One normal measurement or an absence of a particular sound cannot guarantee that pneumonia is absent.
In adults with clinically diagnosed community-acquired pneumonia, UK professionals may use a severity score alongside clinical judgement. In primary care the CRB65 score incorporates confusion, respiratory rate, blood pressure and age. It is designed to help clinicians make decisions about care. Someone at home with frightening symptoms should not try to earn a particular number of points before calling for help.
Does Everyone Need a Chest X-Ray?
A clinician can sometimes make a working diagnosis of pneumonia in the community without an immediate X-ray. The decision depends on the presentation, severity and whether imaging would change management. Hospital assessment is a different setting. NICE recommends processes that allow adults presenting to hospital with suspected community-acquired pneumonia to receive a diagnosis, including chest X-ray, within four hours.
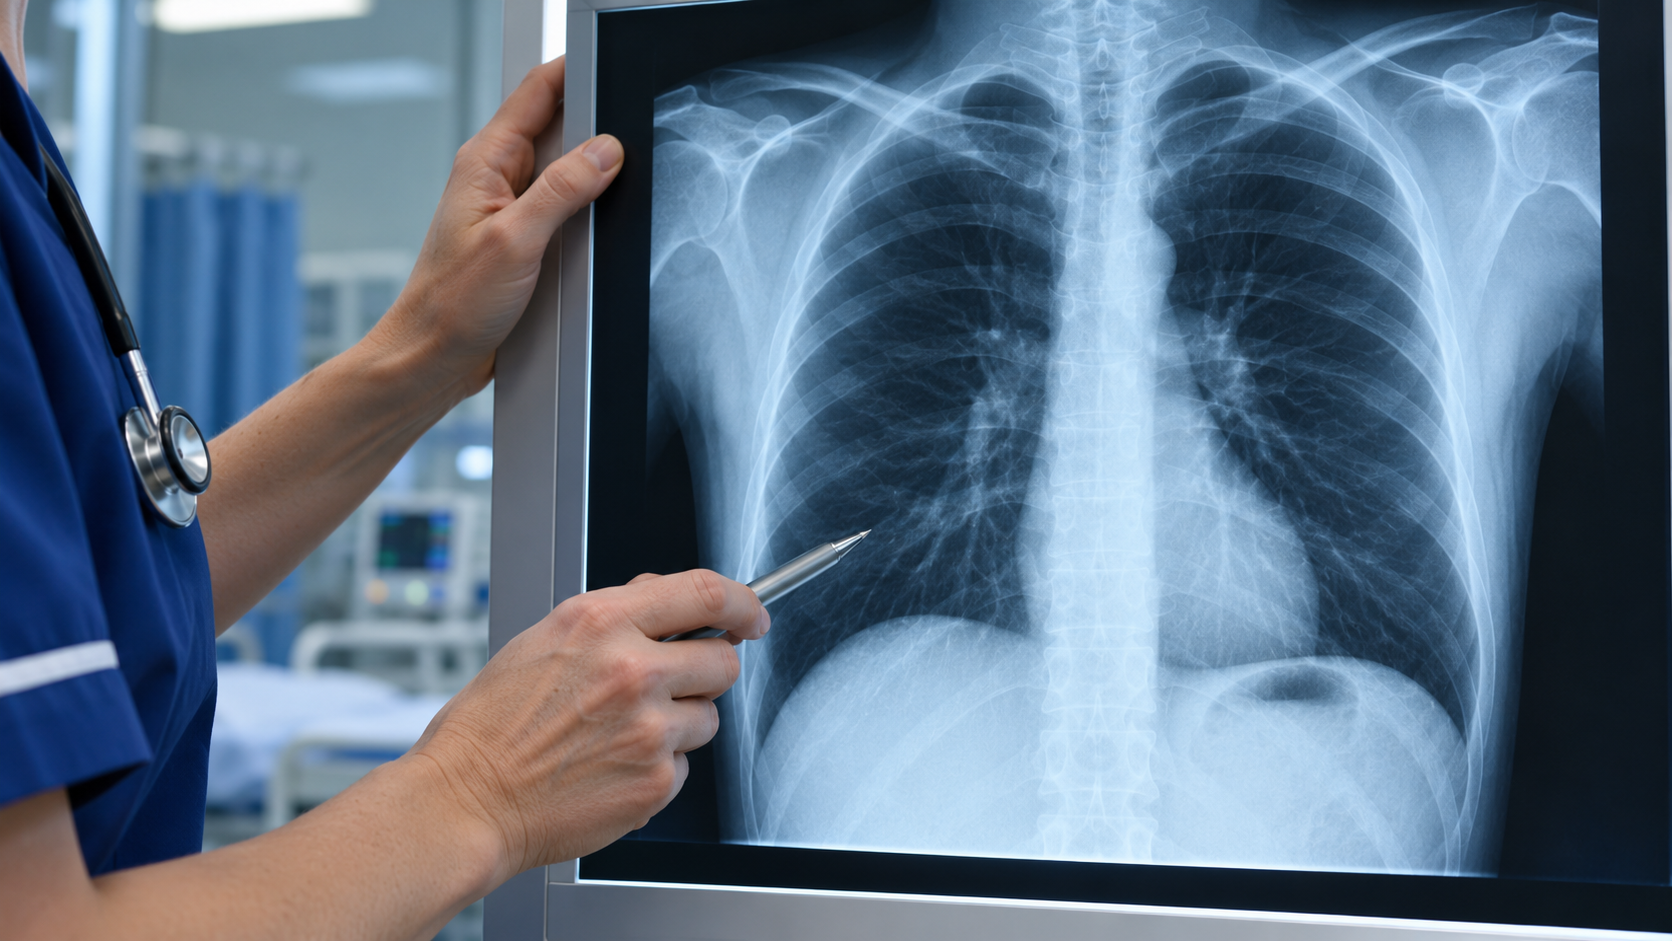
An X-ray uses differences in how tissues absorb radiation to show the lungs and surrounding structures. An area that normally contains air can look denser when inflamed. A picture can help support a diagnosis, identify the extent of changes or prompt consideration of another cause. It does not routinely identify the organism responsible. Two people with similar-looking films may have different treatment needs.
Questions about a repeat film after recovery are separate. Some patients need follow-up imaging, for instance because symptoms persist or risk factors raise concern about an underlying condition. Others do not. A repeat X-ray is a clinical decision about that person’s course. It is possible to be improving while an image still shows changes from a recent infection.
When Are Antibiotics Useful?
Bacteria and viruses can both cause pneumonia. Antibiotics treat susceptible bacteria. They do not treat viruses themselves. When a clinician suspects bacterial pneumonia or cannot safely exclude it in the circumstances, they may prescribe antibiotics. The choice depends on factors including severity, allergies, recent treatment and local guidance. Leftover tablets from another illness are a poor substitute for that assessment.
Many acute chest infections are viral and improve without antibiotics. Green or yellow sputum can occur as the immune system responds to infection. Its colour alone cannot establish that antibiotics are needed. If coloured phlegm accompanies breathlessness, chest pain, deterioration or other concerning symptoms, seek clinical advice about the whole picture.
People treated at home should understand when to expect some improvement and when to contact their clinician again. NHS advice is to contact a GP if symptoms have not started improving after two to three days of antibiotics for pneumonia. Seek help earlier if symptoms worsen. That review may be needed to reassess the diagnosis, complications or the level of support required.
Who Needs Urgent Advice?
Seek an urgent GP appointment or contact NHS 111 if you feel short of breath, have chest pain associated with breathing or coughing, or are worried that a chest infection is getting worse. Babies, older people and those with heart or lung conditions can become seriously ill. Someone with a weakened immune system may also need a lower threshold for advice. Severe breathing difficulty or altered consciousness calls for emergency help.
A useful description for a telephone assessment is concrete. Say what the person could do yesterday and what they can manage now. Being unable to speak in sentences or walk a familiar short distance because of breathlessness conveys more than a number assigned to how ill they feel. Mention relevant diagnoses, medicines and any instructions already given by a clinician.
A home pulse oximeter, if someone has been advised to use one, measures only part of the problem. Movement, cold fingers, poor fit and other factors can affect readings. A reassuring-looking number should never override severe symptoms. Someone with an individual monitoring plan should follow the thresholds agreed with their care team as well as seeking help for deterioration.
What Information Helps When Someone Else Is Making the Call?
If you are ringing for a partner or parent, stay close enough to describe how they are breathing and, if possible, let the clinician speak to them. Have their address, medicines and relevant health conditions to hand. Describe a change against their own usual abilities. Being unable to get from a bedroom to a bathroom can be a striking deterioration for one person and an unhelpful comparison for someone normally supported with mobility.
Ask what should trigger another call if the initial plan is care at home. A clear instruction about worsening breathlessness or new confusion is easier to act on than an assumption that the next appointment is the soonest anyone should hear from you. A planned review does not replace emergency help if the person becomes severely unwell in the meantime.
Why Can Recovery Take Longer Than Expected?
Fever and the immediate feeling of illness may settle before strength and stamina return. The NHS says many people with pneumonia improve within two to four weeks, but recovery varies. Cough, fatigue and reduced exercise tolerance can last longer, particularly after severe disease. A person returning home from hospital may need a different recovery plan from someone whose pneumonia was managed entirely in primary care.
World Pneumonia Day on 12 November draws attention to an illness that can be mild enough for home treatment or serious enough to threaten life. The most useful distinction for a family is the one they can act on. Chest infection describes a broad set of illnesses. Pneumonia identifies one important possibility. If breathing is getting harder, the person is newly confused or a baby will not wake normally, the next step is urgent help, whatever name the illness had yesterday.
